Regulatory Pathway for Intranasal CNS Drug Products at FDA
FDA lacks unified standards for proving drugs reach the brain via nasal delivery.
Intranasal CNS drug development sits at a genuine regulatory frontier, and the reason comes down to a single fact: the mechanism that makes the route scientifically attractive is the same mechanism that standard nasal drug rules were never built to handle. The blood-brain barrier stops most drugs given by injection or pill from ever reaching brain tissue in meaningful amounts; as a result, so much CNS drug development stalls at the barrier itself rather than at the biology of the disease.
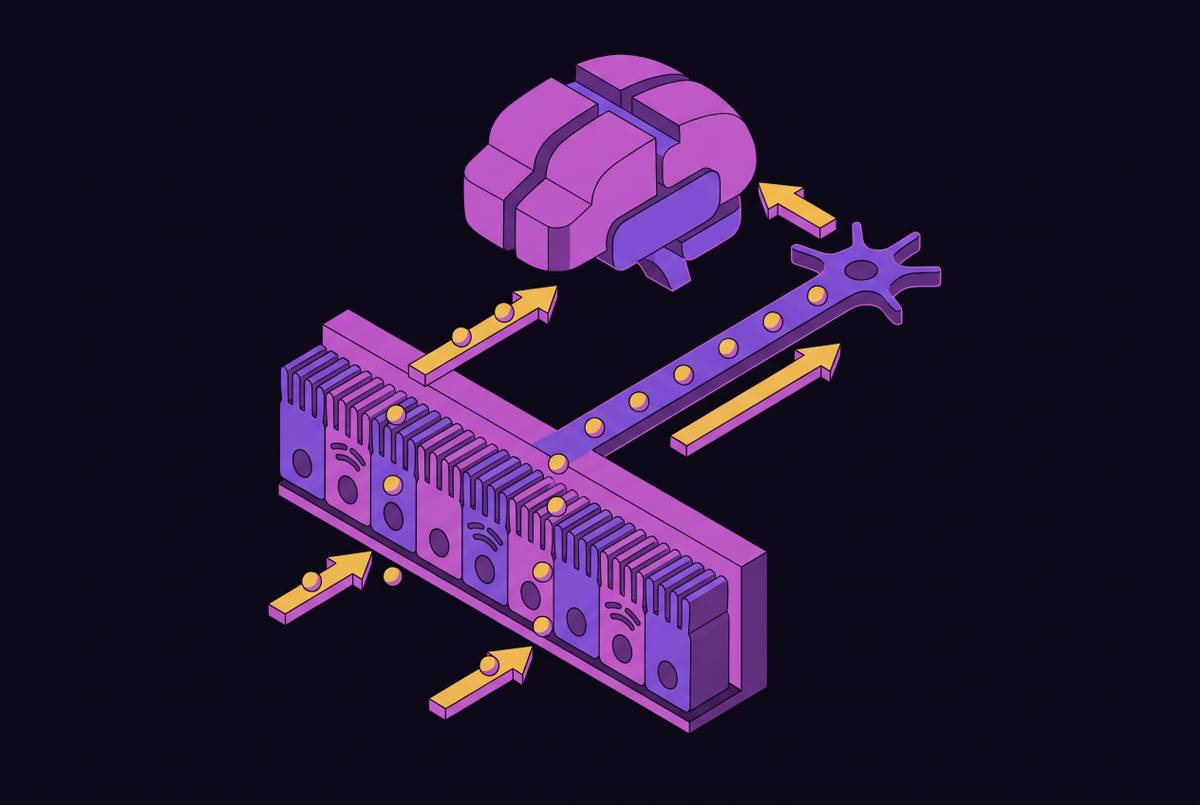
But how does a regulator confirm that a drug found in the brain actually took that path? Drug measured in brain tissue or cerebrospinal fluid after a nasal dose might have traveled along those nerve pathways, but it might also have simply entered the bloodstream through the nasal lining, and from there crossed into the CNS the slow way, through gaps in the barrier that exist in small numbers everywhere. These two routes look identical in a blood sample. Telling them apart takes dedicated measurement built into the study design from day one, and that single ambiguity is the seed of nearly every regulatory difficulty this piece covers: FDA cannot accept a plasma concentration curve as proof that a drug reached the brain by the route a sponsor claims.
None of this is hypothetical. Several intranasal CNS products already have FDA approval: diazepam and midazolam nasal sprays for seizure clusters, triptan sprays for migraine, esketamine (marketed as Spravato) for treatment-resistant depression, and nasal glucagon (Baqsimi) for emergency hypoglycemia. Each demonstrates that the route works in practice. But each one reached the market through its own negotiated set of evidence standards worked out between a sponsor and the agency, not through a single, shared rulebook that the next sponsor can simply follow. That absence of a unified framework is what makes every new intranasal CNS program start closer to a negotiation than a checklist.
Classification of Intranasal CNS Products
Before FDA looks at a single efficacy study, it has to answer a structural question: which part of the product is actually responsible for the clinical effect? Nasal sprays that deliver a prescription drug are classified as drug-device combination products, since they fuse a formulation with hardware, the actuator, the pump, the nozzle, into a single thing the agency has to regulate as one. That classification decision happens early, and it shapes essentially everything that follows in a submission.
FDA sorts out which center leads review by identifying the product's primary mode of action, often shortened to PMOA: the main mechanism through which the combination product produces its clinical effect. The agency has made clear that a single marketing application is appropriate once PMOA is established, so getting this determination right early is not a formality. For most intranasal CNS products, the drug substance is what does the clinical work. That places lead jurisdiction with the Center for Drug Evaluation and Research. That does not let the device off the hook, though. The actuator and nozzle still have to meet device-grade quality and performance standards even when CDER is the lead reviewer, because poor spray performance can undermine the clinical claim no matter which center signs off on it.
One might argue that sponsors can sort out classification informally as a program matures, but the practical consequence argues otherwise. If a sponsor designs a nasal delivery device without engaging FDA early on which center has primary jurisdiction over the product, that device component risks triggering review by a second center, and that adds timelines and submission requirements that are hard to retrofit once a program is underway. Regional divergence compounds the problem. FDA and another regional regulator do not always expect the same things from combination products, and that complicates any plan to run a parallel submission strategy across both regions instead of sequencing them.
FDA's CMC Framework for Nasal Spray Products
Once a product is classified, the chemistry, manufacturing, and controls obligations that follow are specific and unforgiving. FDA last updated its CMC guidance for nasal sprays on January 31, 2025, and that document is the operative standard for any program filing today. It governs how a sponsor characterizes the formulation, sets drug substance and drug product specifications, documents the container closure system (which for a combination product means the device itself), and runs in vitro drug release testing alongside spray pattern, droplet and particle size distribution, plume geometry, delivered dose uniformity, and stability testing.
For nanoparticle-based intranasal formulations, mucoadhesive or surface-modified particle systems designed to stick to and interact with the olfactory epithelium, every one of those CMC parameters gets harder to pin down, because the nanoparticle itself counts as part of the drug product rather than as a passive excipient riding along in the formulation. So before a sponsor ever files an IND, it has to do more characterization work, not less.
CNS programs face one additional wrinkle that a standard decongestant spray never has to think about: where in the nose the drug actually lands. Deposition toward the upper turbinates is associated with olfactory and trigeminal uptake, the neuronal route. But toward the front of the nasal cavity, deposition leads to the bloodstream instead. Which pathway ends up dominating depends heavily on where the spray lands, and FDA expects that distribution to be characterized in vitro using nasal cast models built to approximate human nasal anatomy. FDA leans on a weight-of-evidence approach built on solid in vitro data, but other regulators want case-specific or clinically supported evidence. A sponsor running a US-first strategy can lean harder on in vitro characterization in the early going, but should expect additional clinical data demands to arrive as the program matures.
CNS-specific toxicology and safety standards that standard nasal products do not face
A CNS indication adds a layer of preclinical obligation that a nasal spray aimed at a local or systemic target never triggers, and that layer has to be built into the program from its earliest design rather than bolted on after an IND is already filed. Nasal mucosa tolerability studies have to show that repeated dosing does not damage the olfactory epithelium or impair mucociliary clearance, the two physiological systems that both transport the drug and protect the nose from harm. Damage either one and a sponsor has compromised the delivery mechanism and the safety profile at the same time.
Olfactory nerve toxicity deserves particular attention here, because the olfactory pathway is the direct route to the brain, and the whole approach depends on it. Any formulation ingredient that proves toxic to olfactory sensory neurons threatens two things at once: the delivery mechanism itself, and the patient's sense of smell, a permanent sensory loss that regulators will scrutinize closely. Transport along these nerves runs in both directions, carrying drug toward the brain and also clearing material back out through retrograde movement, and a well-designed toxicology program has to account for that bidirectional traffic rather than assuming the drug simply arrives and stays put.
FDA expects CNS pharmacology studies that go well past what a decongestant or allergy spray program would ever need, characterizing CNS receptor engagement, behavioral effects in animal models, and the potential for CNS-specific adverse events. For peptide and biologic candidates specifically, immunogenicity assessment becomes a required piece of the preclinical package too. Repeated intranasal dosing of a peptide can provoke a mucosal immune response that a small molecule would never trigger, so that risk has to be characterized before Phase I enrollment opens, not discovered partway through a trial.
The evidentiary problem of proving nose-to-brain targeting over systemic absorption
Every earlier section in this piece points toward one unresolved question, and it is the hardest one in the entire framework: how does a sponsor prove that drug reaching the brain got there by the neuronal route rather than by ordinary systemic absorption? FDA cannot accept plasma concentration as a stand-in for CNS targeting, and no standardized method exists yet to make that distinction. Drug Discovery Today, in a September 2026 review, states that standardized regulatory frameworks and solid clinical trials are essential for implementing nose-to-brain delivery strategies, a statement that reads less like encouragement and more like an acknowledgment that the evidence base for direct CNS targeting is still being assembled piece by piece.
What tools does a sponsor actually have to work with? Cerebrospinal fluid sampling offers the most direct evidence of brain exposure, but it is invasive, so it is ethically constrained when the subjects are healthy volunteers rather than patients already undergoing a medically necessary spinal procedure. Pharmacodynamic biomarkers can help, but they are disease-specific and often simply unavailable for a given molecule or indication. Neuroimaging is expensive and remains unvalidated for most drug candidates. Nasal cast deposition studies paired with in vitro permeation data are mechanistically informative and cheap by comparison, but none of them substitute for actual clinical evidence of CNS exposure in a human being.
The ClinicalTrials.gov study NCT06434038 illustrates just how demanding this evidentiary bar has become. The trial measures insulin levels in the cerebrospinal fluid of healthy adults after a single intranasal dose, and that design requires lumbar puncture in volunteers who have no therapeutic need for the procedure themselves. That a sponsor would run a study this invasive says something about how little a developer can take for granted when claiming nose-to-brain delivery, and how far short every indirect method falls of what direct CSF measurement provides. Nanoparticle-based delivery systems add another wrinkle to this picture. Mucoadhesive coatings and ligand attachment are argued to raise the odds of true neuronal transport by strengthening the particle's interaction with the olfactory epithelium, steering uptake toward the olfactory and trigeminal pathways rather than the bloodstream. But an argument about mechanism is not evidence FDA can act on. Demonstrating that claim to the agency still requires the same hard CSF or CNS exposure data that any other intranasal CNS candidate would need to produce.
If a developer cannot design a study that separates the neuronal contribution to brain exposure from the systemic one, the IND meeting will be difficult. That is not a matter of paperwork, but a matter of the agency having nothing concrete to evaluate the central scientific claim against.
Why bioequivalence standards for intranasal rapid-acting drugs remain unresolved
Comparing an intranasal product against a reference drug given by a different route raises a methodological issue of its own, as Wang et al., writing in the Journal of Clinical Pharmacology in 2026, state that FDA has not specifically defined bioequivalence standards for rapid-acting drugs compared across the intranasal and oral routes, and that gap stands in sharp contrast to the well-established bioequivalence criteria that already exist for ordinary generic drug products.
What exactly goes wrong with the conventional approach? Intranasal formulations tend to absorb faster, so you get an earlier onset of action than an oral product carrying the same drug. Standard bioequivalence criteria built around full AUC and Cmax were designed for products that share the same route and similar absorption kinetics, so they do not capture the early-exposure window that gives an intranasal product its clinical edge. Measuring total systemic exposure over the full curve misses the therapeutic advantage the product is actually built around.
Wang et al. propose a partial AUC metric that targets the rapid absorption phase specifically, and they define its cutoff as Tmax plus one standard deviation calculated from the reference product. That is a way of drawing a line around the onset-of-action window instead of averaging it away across hours of total exposure. Because cross-route comparisons carry more inherent variability than same-route comparisons, the proposed acceptance range for the geometric mean ratio of the partial-exposure metric widens to 70% at the lower bound, with a correspondingly raised upper bound, compared with the tighter window used in conventional bioequivalence testing.
For an intranasal CNS program specifically, this methodological gap in cross-route bioequivalence standards compounds the difficulty of proving CNS targeting rather than solving it. A cross-route bioequivalence comparison against an oral reference drug, even a well-designed one using the Wang et al. partial AUC approach, only establishes that systemic exposure is comparable between the two products. It says nothing about whether the intranasal route is actually delivering more drug to the brain, the clinical claim a CNS-targeted product is making. That raises an important question for anyone designing a development program around brain targeting as a differentiator: can bioequivalence data alone ever carry that argument, and the answer is no. A program built on a CNS exposure advantage needs a second, independent evidentiary layer built around proving nose-to-brain delivery, covered earlier in this piece, even after systemic bioequivalence has been established through the newer partial-AUC methods. Comparable blood levels and superior brain delivery are two separate arguments, and FDA requires evidence for both.
Sources
- Bioequivalence Assessment for Intranasal Rapid‐Acting Drug Products - PMC
- Measurement of Insulin Levels in the Cerebrospinal Fluid of Healthy Adults After a Single Intranasal Dose - Middle Age
- Current Clinical Evidence on Nose-to-Brain Drug Delivery - ScienceDirect
- Nasal Spray and Inhalation Solution, Suspension, and ...
- Bioequivalence Assessment for Intranasal Rapid‐Acting Drug Products - Wang - 2026 - The Journal of Clinical Pharmacology - Wiley Online Library