Nose-to-Brain Delivery for CNS-Active Peptides in Preclinical Models
Nasal delivery bypasses the blood-brain barrier for peptides that can't cross it systemically.

Getting a peptide into the brain is a packaging challenge before it is ever a chemistry challenge. The blood-brain barrier keeps out nearly all large biologics by design, and peptides carry a set of properties that stack against them on top of that exclusion. The barrier itself blocks the vast majority of small molecules and essentially all biologics, and peptides add low metabolic stability, poor mucosal permeability, and an inability to survive oral dosing. Each of those weaknesses limits how much drug reaches the brain on its own, and together they push peptide delivery almost entirely into needles.
Switching to subcutaneous injection looks like an obvious fix, since it avoids the stomach and the liver. But it trades one problem for another: the peptide now has to survive systemic circulation and still cross the blood-brain barrier, and brain exposure ends up far below plasma exposure. Drug Discovery News reports that semaglutide administered subcutaneously or orally shows brain-to-plasma partition coefficients (Kp) below 0.0005 to below 0.01. That range reflects extremely limited brain penetration, no matter how much drug circulates in the bloodstream.
What does "good" look like for a CNS peptide delivery system, then? Systemic peptide routes rarely clear that bar. One might argue that simply raising the dose would close the gap. It does not: higher systemic doses raise peripheral exposure and side effects well before they meaningfully raise brain concentrations, which is a structural reason GLP-1 receptor agonist gastrointestinal side effects track so closely with the injection route itself rather than the molecule's inherent toxicity. That is the condition the rest of this piece works against: the constraint is anatomical and pharmacokinetic, not a matter of picking a slightly better molecule or a slightly higher dose.
The olfactory and trigeminal pathways form two distinct conduits to the CNS
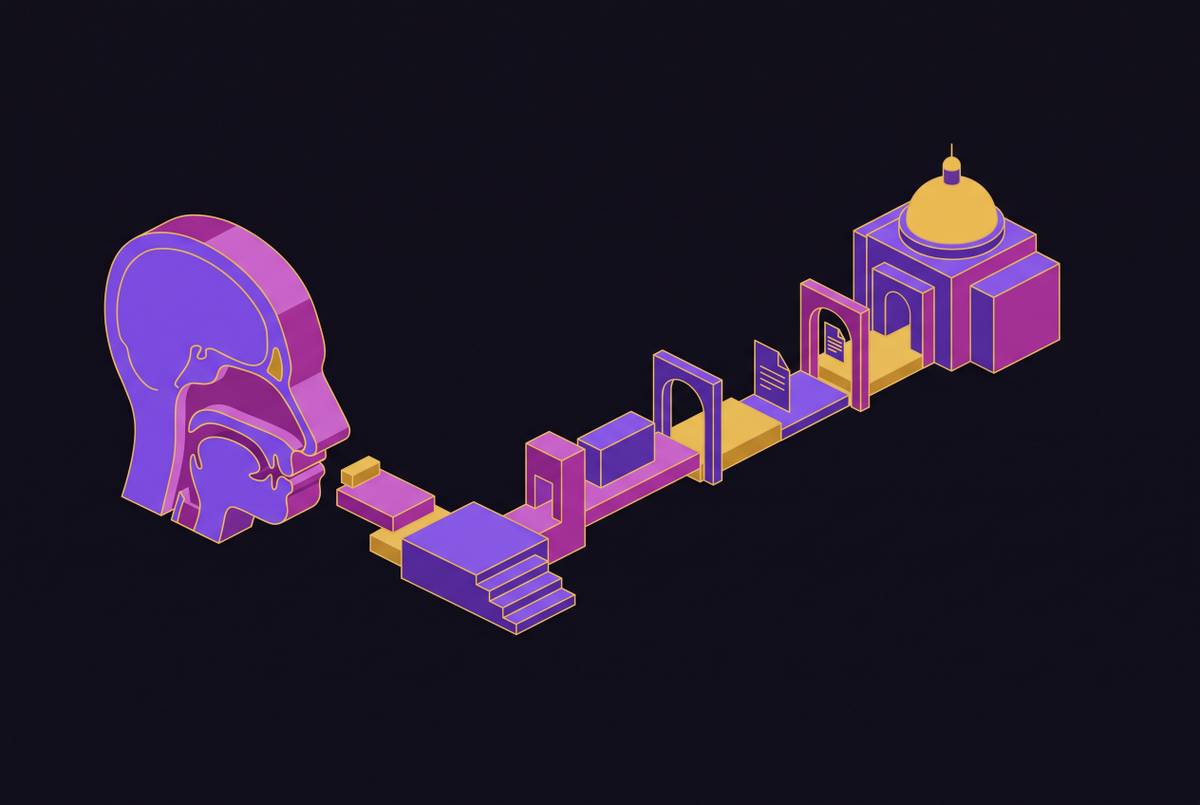
If systemic circulation cannot deliver peptides to the brain in useful concentrations, the nasal cavity offers a different kind of access that does not run through the bloodstream. Two separate nerve networks connect the nose directly to the central nervous system: the olfactory epithelium and the trigeminal nerve. Each works through its own transport mechanism, and a nasal formulation has to be built around whichever one it is trying to use.
The olfactory pathway sits in the upper nasal cavity, where olfactory neurons send axons through the cribriform plate straight into the olfactory bulb. A drug that lands on this tissue can move along those axons (intraneuronal transport) or diffuse through the spaces surrounding the nerves (extraneuronal transport), either way arriving in brain tissue without passing through the blood-brain barrier. This is the most direct anatomical shortcut available, but the olfactory epithelium covers only a small patch of the total nasal surface. Hitting that patch reliably is a device and formulation problem in its own right, not a given just because the tissue exists.
The trigeminal pathway takes a different route. The trigeminal nerve innervates the respiratory epithelium, which makes up the much larger mucosal surface lower in the nasal cavity. Research published in Pharmaceutics by Alabsi and colleagues describes how biomolecules cross into the brain through these trigeminal nerve fibers after intranasal dosing. This pathway also has a distinct destination: it enters the brain at the level of the pons and terminates in the spinal trigeminal nuclei, reaching the brainstem directly. That matters for any condition where the relevant pathology sits in deeper brain structures rather than near the surface. Because the trigeminal-innervated surface is so much larger than the olfactory patch, a formulation that never reaches the olfactory cleft can still achieve real CNS exposure through this route, which makes it the more forgiving target for a standard nasal spray.
These two pathways do not compete with each other. A 2025 review in Translational Neurodegeneration describes how the anatomy of the nose-brain interface supports direct drug transport through both the olfactory and trigeminal routes at once, bypassing the blood-brain barrier entirely. A formulation engineered well enough can engage both pathways simultaneously rather than choosing between them.
The transport along either pathway can happen through several mechanisms: cells taking up the drug and moving it across, diffusion between cells when a permeation enhancer opens the tight junctions, or flow along the spaces that surround blood vessels and nerves. Which mechanism dominates depends on the drug's own chemistry and on whether it is riding inside a nanocarrier.
What separates this whole approach from an injection is the sequence of events. A peptide delivered nasally does not enter the bloodstream first and then attempt to fight its way across the blood-brain barrier. It travels along nerve-associated spaces straight to the CNS, so how much of it sits in plasma and how much sits in brain tissue become partially independent numbers. That decoupling is why a brain-to-plasma ratio above 1 is achievable through the nose in a way that is essentially out of reach for a large peptide given subcutaneously.
What the nasal mucosa does to a peptide before either pathway
Two working pathways to the brain do not mean an easy trip. Before a peptide ever reaches olfactory or trigeminal nerve tissue, it has to survive the nasal mucosa itself, and that tissue applies three separate pressures at once: enzymes that break the peptide down, cilia that sweep it away, and cell membranes that simply will not let much of it through.
The nasal epithelium expresses proteases and peptidases that start cutting peptide bonds on contact. A peptide that is not chemically stable to begin with can lose a substantial fraction of its active structure before it ever reaches the olfactory cleft or the trigeminal-innervated tissue below it. At the same time, the mucosal lining is in constant motion, sweeping deposited material toward the nasopharynx and away from the olfactory region. Without something in the formulation to slow that sweep, a drug's residence time on the mucosa is measured in minutes, which sharply limits how long it has to be absorbed.
Even a peptide that survives both threats still has to get through the epithelial cell membranes themselves, and those membranes are selective in ways that specifically disadvantage hydrophilic compounds and biologics, the exact category most CNS peptides fall into. Hong and colleagues, writing in the International Journal of Pharmaceutics in April 2025, point out that permeation enhancers can raise that permeability, but they come with a safety cost: they can cause irreversible damage to the nasal epithelium, which puts a ceiling on how hard this lever can be pushed.
These three pressures do not act in isolation. Faster mucociliary clearance leaves less time for a drug to cross the permeability barrier, and enzymatic degradation shrinks the pool of intact peptide available to make that crossing even when contact time is extended. Put together, an unformulated peptide sprayed into the nose will not reliably reach therapeutic concentrations in the brain. That has a direct consequence for how preclinical work in this field should be read: a study needs to test an actual formulation, not free peptide, if its results are going to say anything meaningful about the nose-to-brain route. That constraint is what turns nanocarrier design and cell-penetrating peptide strategies from a nice-to-have into the center of the field's preclinical literature: they exist because these three specific barriers demand a specific answer, not as a general upgrade layered onto an otherwise workable delivery method.
How nanocarriers address each mucosal barrier
Nanocarriers respond to the mucosa's three barriers as one connected engineering problem rather than three separate ones, and the preclinical literature shows that the choice of carrier architecture, lipid, polymeric, or hybrid, decides which barrier gets solved and what tradeoff comes with it.
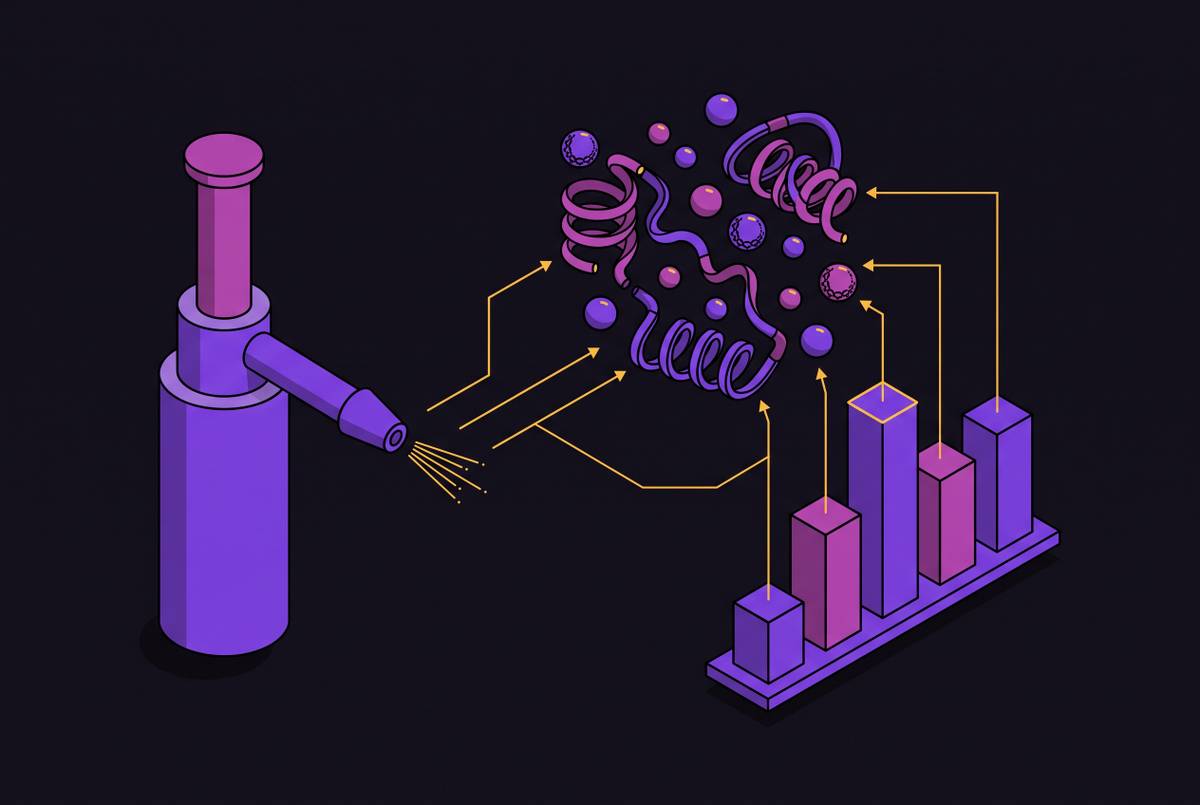
The basic logic is consistent across carrier types. Encapsulating the peptide inside a carrier shields it from the enzymes waiting in the mucosa. Modifying the carrier's surface chemistry can make it stick to the mucus layer longer, slowing the mucociliary sweep that would otherwise clear it out. And the carrier's size and surface charge govern how well it gets taken up by cells or slips between them.
Lipid nanoparticles (LNPs) have drawn particular attention in this space. A 2025 review in Pharmaceutics on nose-to-brain gene delivery describes LNPs as versatile platforms: their composition can be tuned, they can carry a wide range of payloads, and that combination makes them candidates for neurodegenerative disease targets delivered intranasally, including nucleic acid payloads. LNPs also lend themselves well to mucoadhesion, because their lipid surfaces can be modified to bind mucin glycoproteins in the mucus layer, extending residence time beyond what a plain hydrophilic particle would achieve.
Polymeric nanoparticles solve a different piece of the puzzle. They tend to be structurally sturdier than LNPs, and they can be functionalized with targeting ligands on their surface. Attaching those targeting moieties can actively pull the particle across the nasal epithelium and along the neural pathway it is aimed at, rather than relying on passive diffusion alone.
A third category, cell-penetrating peptides (CPPs), offers an alternative to chemical permeation enhancers altogether. Hong and colleagues describe CPPs as a way to get through the epithelial tight junctions without the irreversible tissue damage that comes with harsher chemical enhancers. CPPs are more commonly conjugated directly to the therapeutic agent or nanocarrier than co-administered, because free CPPs are susceptible to oxidation, hydrolysis, and enzymatic degradation in the nasal environment. The benefit of this approach is greater for biologics than for small molecules because biologics face larger size, poorer mucosal permeability, and higher hydrophilicity, the same profile that defines most CNS-active peptides.
One study grounds these design principles in an actual result rather than a general claim. Yang and colleagues built core-shell nanostructures using the cell-penetrating antimicrobial peptide DP7-C wrapped in a hyaluronic acid shell, then dosed them intranasally in vivo. The particles delivered siRNA to the CNS within hours by way of the trigeminal nerve pathway. That result shows the trigeminal conduit can carry an engineered nanocarrier-cargo system beyond its own payload.
None of this works independently of the device delivering it. Bidirectional nasal sprays and precision olfactory delivery (POD) technology have both been shown to improve where drug actually lands in the nasal cavity, and where it lands decides which nerve pathway gets engaged. A formulation built for olfactory targeting needs different device parameters than one built to rely on the trigeminal route, so the carrier and the delivery hardware have to be designed together, not separately.
What should a preclinical result actually be judged on, brain concentration alone, or something else? The more informative number is the brain-to-plasma ratio, not brain concentration by itself. A formulation can raise brain drug levels while raising systemic levels right alongside them, and that outcome does not represent real neural targeting. It also fails to deliver the reduction in peripheral side effects that is supposed to be the whole point of routing a drug through the nose in the first place.
MetP Pharma's 2025 rat data as a benchmark for nasal peptide CNS targeting

The 2025 preclinical rat study from MetP Pharma AG is significant because it achieved a brain-to-plasma ratio above 1 for semaglutide, a result that had not been described for this molecule by any delivery route and that the field uses as the threshold for preferential CNS targeting. Drug Discovery News describes MetP Pharma AG, based in Emmetten, Switzerland and working on nose-to-brain delivery for close to two decades, publishing preclinical data on a nasal semaglutide gel. That gel produced brain-to-plasma ratios consistently above 1, brain exposure that rose with both time and dose in a predictable pattern, and percent-of-injected-dose figures that fall within the range the field considers excellent for a peptide.
Why does crossing that ratio of 1 matter so much? Subcutaneous or oral semaglutide produces Kp values below 0.0005 to below 0.01, so the brain sees only a small slice of what is circulating in plasma. The MetP result represents more than a modest step up from that baseline. It represents flipping the ratio itself, brain exposure now exceeding plasma exposure rather than trailing it by orders of magnitude.
The formulation behind that number relies on two connected pieces: a semi-solid gel matrix and a mono-dose applicator. The gel matrix counters mucociliary clearance by holding the drug against the mucosa longer than a liquid spray would allow, while the applicator controls how much drug goes where in the nasal cavity. The intellectual property behind that combination is patent-protected into 2037 and 2039.
The company is not treating this as a one-molecule result. MetP's pipeline extends the same delivery platform into intranasal therapeutics aimed at concussion, insomnia, ADHD, multiple sclerosis, and hypogonadism, which suggests the underlying technology is being evaluated as a platform once validated on one peptide, rather than as a single-indication product.
Transporter-based systems such as BrainShuttle use receptor-mediated transcytosis and offer a useful comparison for understanding what this approach achieves. Those systems still require intravenous injection, and they are built specifically to raise brain delivery without needing high systemic exposure to do it. Nose-to-brain delivery reaches a similar goal from the opposite direction: rather than maximizing plasma levels and then engineering a way to shuttle drug across the barrier from the blood side, it achieves preferential CNS concentration without ever pushing plasma levels up in the first place. In MetP's framing, low plasma exposure is the mechanism behind reduced peripheral side effects.
That framing extends to how the company argues its data should even be measured. MetP CSO Claudia Mattern has argued that bioavailability calculations based on intravenous comparison are methodologically inappropriate for nose-to-brain technology, since the absence of plasma exposure is a feature of the approach rather than a limitation. Whether that argument reshapes how regulators or other researchers benchmark nose-to-brain data going forward remains an open question. But the rat data behind it give the field something it has not had for this molecule before: a specific, measurable brain-to-plasma ratio above 1, obtained through a named formulation, that other nasal peptide programs now have a concrete number to be measured against.
Sources
- Advances in cell-penetrating peptide-based nose-to-brain drug delivery systems
- Recent Advances in Nose-to-Brain Gene Delivery for Central Nervous System Disorders - PMC
- MetP Pharma’s neural targeting drug delivery technology sets a new benchmark for brain delivery of peptides | Drug Discovery News
- Nose-to-Brain Delivery of Therapeutic Peptides as Nasal Aerosols
- Nose-to-brain drug delivery: from bench to bedside | Translational Neurodegeneration | Springer Nature Link
- Nose-to-Brain Delivery of Therapeutic Peptides as Nasal Aerosols